FOAMed

Preeclampsia and Eclampsia: Common Pitfalls in Diagnosis and Management

The pregnant patient can be challenging to manage in the ED, as we must manage two patients, not just one. Hypertensive disorders in pregnancy affect about 5% to 10% of all pregnancies in the USA. Conditions with hypertension include gestational hypertension, chronic hypertension, preeclampsia, and eclampsia. This post focuses on two of these hypertensive disorders: preeclampsia and eclampsia. How can you avoid the pitfalls in diagnosis and management of these conditions?

Preeclampsia and Eclampsia: Common Pitfalls in Diagnosis and Management Read More »

Penetrating Trauma: What We Miss and How We Can Improve

The patient with penetrating trauma can present with many different injuries. The majority of injuries are easily diagnosed. What about the patient with pneumothorax, diaphragmatic injury, ureteral injury, and hollow viscus injury? These are not so easy to diagnose, and delay in management can cause significant morbidity and mortality. This post provides pearls and pitfalls for these conditions.

Penetrating Trauma: What We Miss and How We Can Improve Read More »

Occult Sepsis in Traumatic Injuries

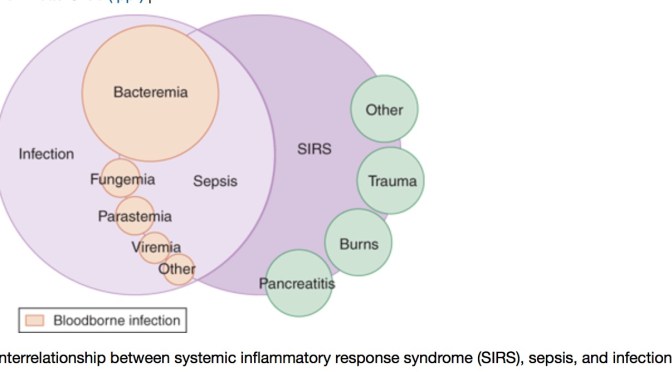
Trauma patients require systematic resuscitation and definitive treatment. However, there are sometimes underlying reasons for the injury, such as syncope prior to the injury or even an underlying infection that made him or her prone to injury. Not all trauma patients will be unstable from their injury and they may have underlying comorbidities that need to be uncovered and treated. This article reviews some basic steps that can be taken to evaluate for underlying infection in trauma patients.

Occult Sepsis in Traumatic Injuries Read More »

Troubleshooting G-tubes & J-tubes: Common scenarios / Tips & Tricks

There are many types of surgically placed feeding tubes, including both gastrostomy (G) and jejunostomy (J) tubes. Complications with these tubes are commonly seen in the emergency department and this article provides a general overview of these complications and how they can be quickly and easily managed by the emergency physician.

Troubleshooting G-tubes & J-tubes: Common scenarios / Tips & Tricks Read More »

R.E.B.E.L. EM – How to Call a Consult

The Bottom Line
Learning to call effective consults that will facilitate faster dispositions for our patients is an essential skill for every emergency physician to master
Using the 5C framework is an effective way to both model, and teach effective consultation
Leading your consult call with a specific question will make the call a lot easier. If you are about to deliver 20 data points, and your consultant only needs 5, they will be able to pick those 5 from the 20 you offer them, but only if they know the question up front. This will save you from having to repeat these data points to the consultant
More attention needs to be paid to the way we arrange consultations, as they can be a significant source of frustration, conflict, and job dissatisfaction if not performed efficiently and correctly.

R.E.B.E.L. EM – How to Call a Consult Read More »

Dr. Strangelove or How I Learned to Stop Worrying and Sit on the qSOFA: A pathophysiologic approach to qSOFA

The last few months have seen an enormous amount of controversy in the press, in the FOAMsphere, and in our ED hallways regarding the new consensus sepsis definition. The goal of this post is not to rehash the strengths and weaknesses of Sepsis 3, but rather to explore the pathophysiologic basis of the simplified clinical features of sepsis outlined in the qSOFA score, which might explain why the definition shook out the way it did. Hopefully, such an understanding will help us apply lessons learned from the derivation of Sepsis 3 to the management of these profoundly sick patients.

Dr. Strangelove or How I Learned to Stop Worrying and Sit on the qSOFA: A pathophysiologic approach to qSOFA Read More »

Commonly Missed Findings on CT Abdomen/Pelvis

CT: the donut of truth. Most physicians breathe a little easier sending a patient home with a negative CT abdomen/pelvis. However, the power of x-ray vision doesn’t allow us to turn off our brains. Certain pathologies may have only subtle findings on CT, and others may lend themselves better to other imaging modalities, such as ultrasound. By being aware of these pathologies and how to identify them, we can better recognize patients at risk of a missed diagnosis.

Commonly Missed Findings on CT Abdomen/Pelvis Read More »